
041 001 0394Life St George's Hospital · Gqeberha, 6001Mon–Thu 08:00–17:00 · Fri 08:00–13:00
Services · Sports Medicine

Athletic injuries

Many athletes injure their knee ligaments. Of the four major ligaments in the knee, the ACL and MCL are injured most often in sport.

Many athletes experience injuries to their knee ligaments. Of the four major ligaments found in the knee, the anterior cruciate ligament (ACL) and the medial collateral ligament (MCL) are often injured in sports. The posterior cruciate ligament (PCL) may also be injured.

Pain, in any form, can range from a mild annoyance to completely debilitating. To one degree or another, it keeps you from living a full and active life. You may have chronic pain from an injury, or a condition such as osteoarthritis. Either way, there are options to get you back to your best health.

Request an Appointment
Sports medicine: athlete's knee treated at Dr Gerhard Pienaar's practice

Knee Ligament & Meniscal Injuries

Knee ligament and meniscal injuries are common following sport, twisting injuries, falls and direct trauma. They can range from minor sprains that recover with rehabilitation to significant injuries causing ongoing instability and requiring surgery.

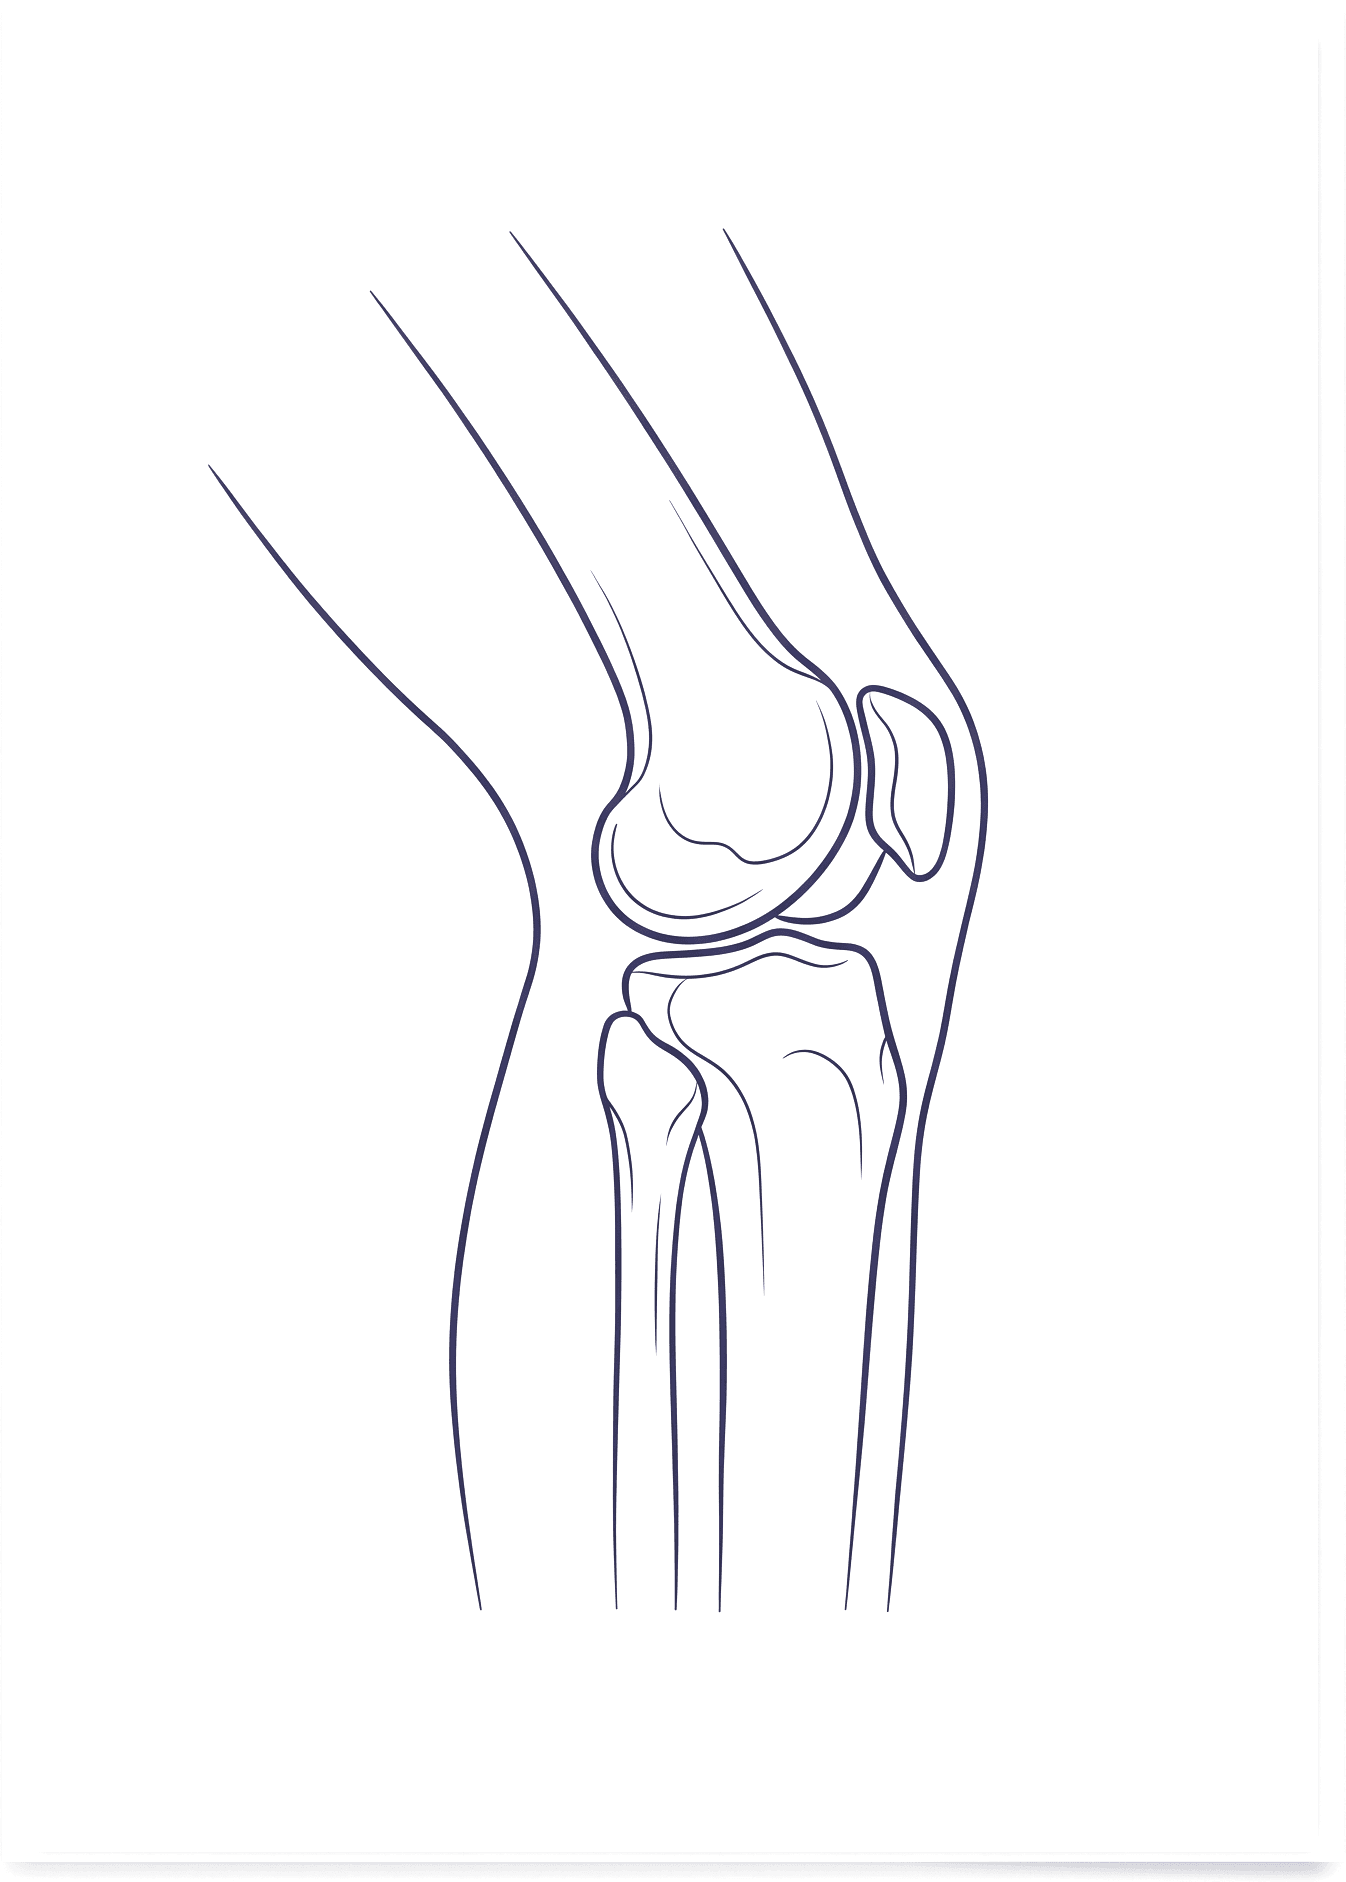
The knee contains several important stabilising ligaments as well as two menisci, which help distribute load and protect the joint.

ACL – Anterior Cruciate Ligament Injury

The anterior cruciate ligament (ACL) is one of the main stabilising ligaments of the knee. It controls forward movement of the tibia and provides important rotational stability.

ACL injuries commonly occur during sport with sudden changes in direction, pivoting, twisting or awkward landings. Patients may feel or hear a "pop", followed by swelling and a sensation that the knee is unstable or gives way.

Treatment

Treatment depends on age, activity level, sporting requirements, associated injuries and the degree of instability.

Some patients can be managed with structured physiotherapy and rehabilitation. In active patients, athletes or those with recurrent instability, ACL reconstruction may be recommended. Associated meniscal or cartilage injuries can often be treated during the same procedure.

PCL – Posterior Cruciate Ligament Injury

The posterior cruciate ligament (PCL) prevents excessive backward movement of the tibia and is an important stabiliser of the knee.

PCL injuries commonly occur after a direct blow to the front of the knee, a fall onto a bent knee or higher-energy trauma.

Treatment

Many isolated PCL injuries can be successfully treated without surgery using a specialised rehabilitation programme and, in selected cases, a brace.

PCL reconstruction may be considered when there is significant ongoing instability, a high-grade injury or injury to several knee ligaments.

MCL – Medial Collateral Ligament Injury

The medial collateral ligament (MCL) is located on the inner side of the knee. It provides stability against forces pushing the knee inward.

MCL injuries commonly occur during contact sports when a force is applied to the outside of the knee.

Treatment

Most isolated MCL injuries have good healing potential and can be treated without surgery using a brace when required, followed by physiotherapy and progressive return to activity.

Surgery may be required for selected severe injuries or when the MCL injury occurs together with other ligament injuries.

LCL – Lateral Collateral Ligament Injury

The lateral collateral ligament (LCL) is situated on the outer side of the knee and helps provide side-to-side stability.

LCL injuries are less common than MCL injuries. Significant LCL injuries may occur together with damage to other structures on the outer and back part of the knee.

Treatment

Minor isolated injuries can often be treated with bracing and rehabilitation.

More significant injuries causing instability, particularly when associated with other ligament injuries, may require surgical repair or reconstruction.

PLC – Posterolateral Corner Injury

The posterolateral corner (PLC) consists of a group of ligaments and tendons on the outer and back part of the knee. These structures provide important rotational and side-to-side stability.

PLC injuries usually result from significant trauma or twisting injuries and may occur together with ACL or PCL injuries.

Treatment

Minor isolated injuries may sometimes be managed with bracing and rehabilitation.

Higher-grade PLC injuries causing instability frequently require surgical repair or reconstruction, particularly when other knee ligaments are also damaged.

Meniscal Tears

The knee contains two menisci – the medial meniscus and lateral meniscus. These specialised cartilage structures act as shock absorbers, distribute load across the knee and contribute to joint stability.

Meniscal tears may occur following a twisting injury during sport or develop gradually as part of degenerative changes within the knee.

Symptoms can include joint-line pain, swelling, clicking, catching or locking.

Treatment

Not every meniscal tear requires surgery. Many tears, particularly degenerative tears, can initially be managed with activity modification, medication and physiotherapy.

When surgery is required, treatment is usually performed using keyhole surgery (knee arthroscopy).

Whenever possible, the aim is to preserve and repair the meniscus rather than remove it. Meniscal repair is particularly important in younger patients and suitable traumatic tears. Tears that cannot be repaired may require removal of only the unstable damaged portion of the meniscus.

When Should I See an Orthopaedic Surgeon? (Knee)

An assessment is recommended if you experience:

How Are Knee Soft-Tissue Injuries Diagnosed?

Diagnosis starts with a detailed history and clinical examination. X-rays may be performed to exclude fractures or assess the joint, while an MRI scan can provide detailed information about the ligaments, menisci, cartilage and other soft tissues.

Not every knee injury requires an MRI, and the appropriate investigations will depend on the clinical findings.

Individualised Treatment

There is no single treatment that is appropriate for every knee injury.

Management depends on the structures injured, severity of the injury, degree of instability, age, occupation, sporting requirements and the patient's individual goals.

Whenever possible, treatment aims to preserve the natural structures of the knee, restore stability and function, and allow a safe return to normal activities and sport.

  • Significant swelling following a knee injury
  • A "pop" or tearing sensation at the time of injury
  • Difficulty putting weight on the leg
  • Repeated giving way or instability
  • Persistent pain despite rest and rehabilitation
  • Catching or locking of the knee
  • Difficulty fully straightening or bending the knee
  • Inability to return to sport or normal activities

Hip Soft-Tissue Injuries

Hip pain is not always caused by arthritis or problems with the bones. The hip is surrounded by important soft-tissue structures, including the labrum, cartilage, tendons and muscles, all of which can be a source of pain or injury.

Soft-tissue hip problems may develop following a sporting injury, repetitive activity or gradually over time.

Hip Labral Tears

The labrum is a ring of specialised cartilage surrounding the edge of the hip socket. It helps maintain hip stability, distributes load and contributes to the normal function of the joint.

Labral tears may occur following a twisting or sporting injury but commonly develop because of abnormal contact between the ball and socket of the hip, particularly in patients with femoroacetabular impingement (FAI).

Symptoms may include deep groin pain, clicking or catching, stiffness and pain with prolonged sitting, exercise or rotational movements.

Treatment

Initial treatment may include activity modification, anti-inflammatory medication and specialised physiotherapy.

Persistent symptoms may require further investigation and, in selected patients, hip arthroscopy. During arthroscopy, the labrum can often be repaired while associated abnormalities contributing to the tear can be addressed at the same time.

Femoroacetabular Impingement (FAI)

Femoroacetabular impingement, or FAI, occurs when the shape of the ball or socket causes abnormal contact within the hip during movement.

The two main forms are CAM impingement, involving additional bone at the femoral head-neck junction, and pincer impingement, involving increased coverage of the femoral head by the socket. Some patients have a combination of both.

FAI may contribute to labral and cartilage damage over time.

Typical symptoms include groin pain, reduced hip movement and discomfort during deep flexion, squatting, twisting or prolonged sitting.

Treatment

The presence of a CAM or pincer shape on an X-ray does not automatically require treatment. Treatment is generally directed at patients who have symptoms.

Initial management usually involves activity modification and physiotherapy. In patients with persistent symptoms and suitable joint anatomy, hip arthroscopy may be considered to treat the impingement and repair associated labral damage.

Gluteal Tendon Injuries & Greater Trochanteric Pain Syndrome

Pain over the outside of the hip is commonly referred to as Greater Trochanteric Pain Syndrome (GTPS).

Although this was traditionally called "trochanteric bursitis", pain in this area is frequently related to the gluteus medius and gluteus minimus tendons, which attach to the outer aspect of the hip.

Problems range from tendon irritation and degeneration to partial or complete tendon tears.

Patients typically experience pain on the outside of the hip, particularly when walking, climbing stairs or lying on the affected side.

Treatment

Most patients can initially be treated without surgery using activity modification, appropriate medication and a structured physiotherapy programme focusing on the gluteal muscles and hip mechanics.

Injections may be useful in selected patients.

Persistent symptoms or significant gluteal tendon tears may require surgical repair, which can be performed arthroscopically or through an open approach depending on the type of tear.

Hip Flexor & Iliopsoas Problems

The iliopsoas is a powerful hip flexor located at the front of the hip.

Overuse, repetitive activity or sporting injuries can cause irritation of the muscle or tendon. Some patients develop a snapping sensation at the front of the hip, sometimes referred to as an internal snapping hip.

Symptoms usually include pain in the front of the hip or groin, particularly when lifting the leg, climbing stairs or performing repetitive hip-flexion activities.

Treatment

Treatment usually includes activity modification, physiotherapy, stretching and strengthening.

Injections can occasionally assist with diagnosis and treatment. Surgery is rarely required but may be considered for persistent symptoms that do not respond to appropriate conservative treatment.

Proximal Hamstring Injuries

The hamstring tendons originate from the lower part of the pelvis and are particularly important during running, sprinting and acceleration.

Injuries range from minor muscle strains to partial tendon injuries and complete tendon avulsions from the pelvis.

Patients may experience sudden pain in the buttock or back of the thigh, bruising, weakness or difficulty running.

Treatment

Most minor and partial injuries can be successfully managed with physiotherapy and progressive rehabilitation.

Complete tendon avulsions and selected significant partial tears may require surgical repair, particularly in active patients.

Adductor & Groin Injuries

The adductor muscles are situated along the inner thigh and play an important role in hip stability and sporting activities involving running, kicking and rapid changes in direction.

Adductor injuries commonly occur during sport and can range from minor strains to significant muscle or tendon injuries.

Groin pain may also originate from the hip joint itself, the abdominal wall or other surrounding structures, making an accurate diagnosis important.

Treatment

Most adductor injuries are treated with activity modification followed by progressive physiotherapy, strengthening and return to sport.

Persistent groin pain requires further assessment to identify the underlying cause before additional treatment is considered.

When Should I See an Orthopaedic Surgeon? (Hip)

Assessment is recommended if you experience:

How Are Hip Soft-Tissue Problems Diagnosed?

Diagnosis starts with a detailed history and clinical examination.

X-rays are important for assessing the shape of the hip joint and identifying conditions such as FAI, hip dysplasia or arthritis.

An MRI scan may be used to assess the labrum, cartilage, tendons and surrounding soft tissues. In selected patients, specialised imaging or diagnostic injections may also be useful.

Not every patient with hip pain requires an MRI, and investigations should be guided by the clinical findings.

Individualised Treatment

Many hip soft-tissue conditions can be successfully treated without surgery.

Treatment may include activity modification, medication, specialised physiotherapy and selected injections.

When symptoms persist despite appropriate conservative treatment, surgery may be considered. Depending on the underlying condition, this may include hip arthroscopy, labral repair, correction of femoroacetabular impingement or repair of damaged tendons.

The aim of treatment is to identify the underlying cause of the patient's symptoms, preserve the natural hip joint whenever possible and restore comfortable movement and function.

  • Persistent hip or groin pain
  • Pain that limits sport, exercise or normal daily activities
  • Clicking, catching or locking associated with pain
  • Significant loss of hip movement
  • Persistent pain despite physiotherapy
  • Pain on the outside of the hip that makes sleeping difficult
  • Weakness or difficulty walking
  • Sudden severe pain or bruising following a sporting injury

An active, pain-free life is the goal

Whether your pain comes from an injury or a condition such as osteoarthritis, there are options to get you back to good health.

Request an Appointment